Ultrasound-Guided Hydrodissection
Releasing a trapped nerve with fluid instead of a scalpel
Some pain does not come from a joint or a tendon - it comes from a nerve that has become trapped, compressed or stuck to the tissue around it. The result: burning, tingling, electric sensations, numbness, or pain that follows the path of the nerve.
Hydrodissection is a minimally invasive, ultrasound-guided procedure in which fluid is injected precisely around the nerve, gently separating it from the surrounding tissue and relieving the mechanical irritation.
No incision. No scar. A procedure measured in minutes - with the needle guided in real time by ultrasound.
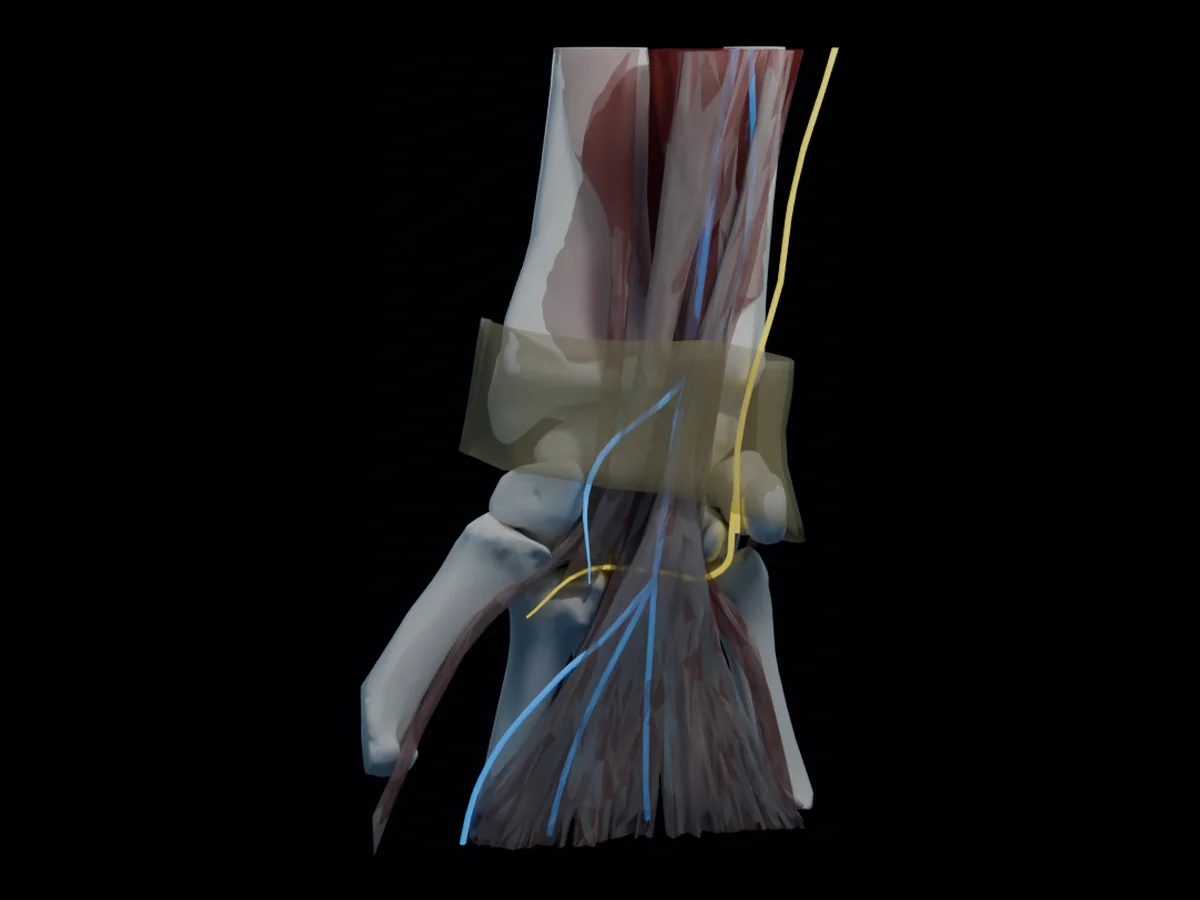
What the model shows: 3D model of the palm side of the right wrist in Julio: the carpal bones, the flexor tendons and the transverse carpal ligament shown transparent, with the median nerve highlighted in blue inside the carpal tunnel and the ulnar nerve beside it. Julio, Team Clinic 360° Anatomical detail: In blue: the median nerve inside the carpal tunnel. The transparent "roof" above it is the flexor retinaculum, and the flexor tendons run beside it. When the space in the tunnel narrows, the nerve is what gets compressed, and that is exactly where hydrodissection comes in. Interaction: this is an interactive 3D model from Julio. Once the 3D view loads it rotates automatically, unless the device is set to reduce motion. Drag to change the viewing angle and examine the anatomy from different sides; after you start interacting you can also zoom in and out.
In blue: the median nerve inside the carpal tunnel. The transparent "roof" above it is the flexor retinaculum, and the flexor tendons run beside it. When the space in the tunnel narrows, the nerve is what gets compressed, and that is exactly where hydrodissection comes in.
Anatomy model from Julio, the Team Clinic 360° digital atlas. Geometry sources: BodyParts3D © The Database Center for Life Science, CC BY-SA 2.1 JP; Z-Anatomy, CC BY-SA 4.0.
What is nerve hydrodissection?
Nerves are meant to glide freely as we move. After injury, overuse, surgery or chronic inflammation, a nerve can become tethered - compressed by fascia, scar tissue or swollen neighboring structures. Every movement then pulls and irritates it.
In hydrodissection, the physician uses a fine needle, under continuous ultrasound visualization, to inject fluid (typically a dilute local anesthetic solution, sometimes with additional agents) into the plane around the nerve. The fluid does the work: it separates the nerve from the tissue compressing it and restores its ability to glide.
Which problems can it address?
In suitable cases, hydrodissection may be considered for:
- Carpal tunnel syndrome (median nerve at the wrist)
- Ulnar nerve irritation at the elbow - often alongside golfer's elbow
- Radial nerve entrapments near the elbow
- Nerve pain after surgery or injury, related to scar tissue
- Selected entrapments in the shoulder, hip, knee and ankle regions
- Persistent, localized nerve pain where imaging and examination point to a specific entrapped nerve
The essential precondition is a precise diagnosis: identifying the exact nerve, and the exact site where it is caught. That is what the clinical exam and diagnostic ultrasound are for.
What happens during the procedure?
- The region is scanned with ultrasound and the nerve is identified
- The skin is cleaned and numbed locally
- Under continuous ultrasound guidance, a fine needle is advanced to the plane beside the nerve
- Fluid is injected slowly; on the screen, the nerve can be seen separating from the surrounding tissue
- The needle is withdrawn - typically after only a few minutes
Most patients go home shortly afterwards and return to light normal activity the same day. Mild local soreness for a day or two is common; some feel a change in symptoms quickly, while for others improvement builds gradually over days to weeks.
Why choose this before considering surgery?
Surgical release remains the right answer for some severe entrapments. But for many patients, hydrodissection offers a rational earlier step:
- Minimally invasive - no incision, no scar, no recovery period to speak of
- Diagnostic value - the response to the procedure itself sharpens the diagnosis
- Repeatable when appropriate
- Leaves every future option open
At Team Clinic 360°, hydrodissection is performed by Dr. Lior Shem Tov, specialist in anesthesiology and pain medicine, as part of a plan coordinated by Dr. Natalie Siegel.
Nerve pain with a mechanical cause deserves a mechanical answer
If you have burning, tingling or electric pain that follows a nerve - and treatments so far have only masked it - an evaluation can determine whether an entrapped nerve is the cause, and whether hydrodissection can release it.
To schedule an evaluation for ultrasound-guided hydrodissection - contact us by phone or WhatsApp.
Where can a peripheral nerve become trapped?
Peripheral nerves travel through narrow passages beneath ligaments, between muscles and around bony landmarks. These are common sites of entrapment. The examples below translate the clinical explanations on our Hebrew hydrodissection page. They help explain the anatomy; they are not a diagnosis or a recommendation to treat every symptom with an injection.
The ulnar nerve at the elbow
The ulnar nerve passes behind the inner bony prominence of the elbow, often called the funny bone. Entrapment there can cause elbow pain extending down the inner forearm, tingling in the ring and little fingers, and weakness affecting those fingers. Ultrasound can also show whether the nerve moves over the prominence as the elbow bends. The location of the symptoms and the nerve's behavior during movement both contribute to the evaluation.
The suprascapular nerve at the shoulder
This nerve passes through a notch at the top of the shoulder blade and then around another notch toward its back. Compression at the upper notch can cause deep shoulder pain and weakness when lifting or rotating the arm outward. Compression farther along the nerve may cause wasting of a muscle at the back of the shoulder blade, sometimes without pain. Identifying the site matters because shoulder pain can involve different structures and does not automatically mean a nerve is trapped.
Meralgia paresthetica: burning in the outer thigh
The lateral femoral cutaneous nerve leaves the pelvis beneath the inguinal ligament, near the front of the pelvis. Compression can produce burning, tingling or numbness on the front and outer thigh, often worse while standing and easier while sitting. This nerve carries sensation rather than controlling leg muscles. Leg weakness therefore calls for evaluation of other causes, including the lower back. Many cases respond to conservative treatment. If symptoms persist, the examination determines whether treatment around the nerve is appropriate.
The sciatic nerve in the deep buttock
After leaving the pelvis, the sciatic nerve passes beneath the piriformis muscle and alongside other small muscles deep in the buttock. Pressure in this region can cause deep buttock pain that travels down the back of the leg and worsens with prolonged sitting, especially on a hard surface. It can resemble pain originating in the lower back. Both problems can also coexist, so the evaluation considers both rather than choosing a treatment solely from where pain is felt.
The common fibular nerve at the knee
This nerve runs around the head of the fibula on the outer side of the knee, with little tissue protecting it. It can be vulnerable to pressure from prolonged leg crossing, a cast or injury. Injury to the nerve may cause weakness in lifting the foot and toes. Such weakness needs prompt medical evaluation. The purpose of explaining this anatomy is to clarify why symptoms need assessment, not to suggest that hydrodissection is always the right response.
Similar symptoms can have different sources
A trapped nerve in a limb can resemble a problem in the spine. Pain and tingling from the neck may mimic carpal tunnel syndrome or ulnar nerve entrapment. Lower-back problems may resemble meralgia paresthetica or irritation of the sciatic nerve in the buttock. Treating the wrong site may leave the original problem unresolved. When needed, assessment therefore includes the neck and back, nerve conduction studies or EMG, and imaging.
Before deciding on hydrodissection, the clinician reviews the pain history, its location and character, what worsens or eases it, previous treatments, medical conditions, medicines and available test results. The first question is whether the symptoms genuinely suggest a peripheral nerve that can be treated at a specific site. Sometimes a nerve block, rehabilitation, medication or further investigation is more appropriate.
Why ultrasound and follow-up matter
Small distances matter around peripheral nerves. Ultrasound allows the physician to see the nerve, needle, vessels and tendons in real time rather than rely solely on estimated anatomical position. It also contributes to diagnosis: the median nerve can be assessed beside the flexor tendons at the wrist, and movement of the ulnar nerve can be observed at the elbow. The physician plans an approach based on the structures actually seen.
The fluid is chosen according to the diagnosis, location, sensitivities and purpose of the procedure. A suitable medicine may sometimes be included. The expected response, alternatives and follow-up instructions should be discussed individually. Hydrodissection does not suit every nerve pain problem, guarantee pain relief or replace a medical assessment.
Responses vary. Some people notice change quickly; others improve gradually, and some do not obtain sufficient relief. Temporary local tenderness, pressure, fullness or altered sensation may occur. If improvement is insufficient, the diagnosis and ongoing plan are reconsidered. Depending on the case, care may include rehabilitation, physiotherapy, changes in loading or medication.
At Team Clinic 360°, pain and rehabilitation perspectives are considered together. In appropriate cases two specialists assess the patient in the same room. The goal is to understand the source of the problem and choose a suitable plan. For consultation, bring available imaging, EMG results, earlier consultation summaries, a medicine list and a clear description of the pain, radiation and numbness.
Frequently asked questions
Does hydrodissection hurt?
The skin is numbed first, and the injection is slow and controlled. Patients typically describe pressure or brief odd sensations along the nerve rather than sharp pain.
How is this different from a cortisone injection?
A cortisone injection treats inflammation chemically. Hydrodissection treats compression mechanically - the fluid physically separates the nerve from what is pressing on it. In some cases the two approaches are combined.
How many treatments are needed?
Some patients respond well to a single procedure; others benefit from a short series. The plan depends on the nerve involved, the severity of the entrapment and your response.
Can it replace carpal tunnel surgery?
In milder and moderate cases it can be an effective alternative or a way to defer surgery; in severe cases with significant weakness or muscle loss, surgery may still be the right choice. This is exactly what the evaluation clarifies.
Is it safe?
Performed under continuous ultrasound guidance by an experienced physician, hydrodissection is considered a low-risk procedure. The visible needle path and real-time control are precisely what makes it safe.
Medical sources for further reading
The information on this page is intended as general background and does not replace personal medical advice.
The information on this page is general in nature and does not replace a personal medical diagnosis, consultation or treatment. Any treatment is tailored only after a medical evaluation, at the physician's discretion.